
Report says new CMS payment model for heart failure is 'remarkably bad' and could harm patients
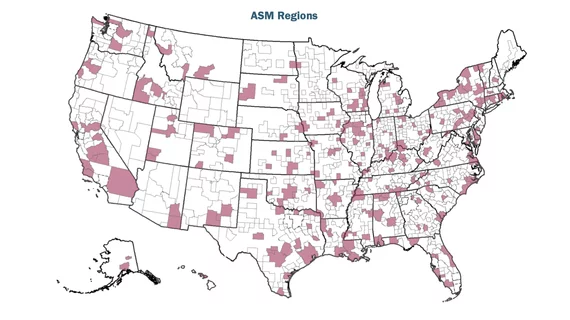
There were serious concerns in early 2026 when 2,600 general cardiologists were surprised to find out they are required to participate in a new mandatory Medicare Ambulatory Specialty Model (ASM) for heart failure starting Jan. 1, 2027. Now a new report from the Center for Healthcare Quality and Payment Reform (CHQPR) says the ASM will reduce access to care for tens of thousands of Medicare beneficiaries, increasing Medicare spending rather than produce savings.
CHQPR is a source of unbiased information and assistance on payment and delivery policies in an effort to facilitate reform. The group has provided information and technical assistance to Congress, federal agencies such as the U.S. Centers for Medicare and Medicaid Services (CMS) and MedPAC and national organizations such as the American Medical Association (AMA) and the American Hospital Association (AHA).
The ASM program is aimed at heart failure and lower-back pain management, both of which are high cost drivers in the Medicare program. Thousands of physicians who treat these patients were notified earlier in 2026 they were required to participate. The American College of Cardiology (ACC) determined later that many of the cardiologists included should have never been a part of the program based on the states requirements. The ACC also noted that many people on the list were unaware they were part of the program. In addition, details about how to participate can be hard to find.
"This is a remarkably bad program that has gotten far too little attention, partly because it’s been buried in the hundreds of pages of the Medicare Physician Fee Schedule regulations, and partly because the program is so complicated that the problems with it are difficult to see," Harold D. Miller, president and CEO of CHQPR, and adjunct professor of public policy and management at Carnegie Mellon University, told Cardiovascular Business.
He said the program is unique because it is the first Medicare physician payment model that includes a “redistribution percentage” less than 100%. Unlike the MIPS program, more physicians in ASM will receive payment reductions than increases. Miller said this was done solely so that the CMS Center for Medicare and Medicaid Innovation (CMMI) could ensure the program reduced Medicare spending.
"Most other CMMI models have ended up increasing Medicare spending rather than producing savings, so CMMI is trying to tilt the scale in its favor in this model," Miller explained. "Unlike MIPS and other CMMI programs, ASM has no predefined performance standard or target that physicians are expected to meet – they will get a pay cut if they get a slightly lower score than the majority of the other physicians in ASM, even if they are delivering high-quality care and even if they improved their performance compared to the prior year."
Most cardiologists under the ASM will see pay cuts
The CHQPR report outlines that the net result will be the majority of physicians in the program will see their payments cut. The organization said pay cuts will serve as a disincentive for the physicians forced into the program to treat heart failure patients at all. Often, general cardiologists may not be treating a large number of heart failure patients, but under this program, low performance scores for even these handfuls of patients may impact their payments overall. There is also no way for any physician to know what they could do to avoid a cut, Miller explained.
The CHQPR report states payment cuts could be as high as 9%.
"This is hardly an incentive to improve care," Miller said.
Physicians may stop seeing heart failure patients
The only way doctors can avoid these cuts is to stop providing services to Medicare beneficiaries with heart failure or low back pain. The report raised concerns that this could reduce access to care for tens of thousands of Medicare beneficiaries. If that happens, beneficiaries with heart failure or low back pain will find it much more difficult to obtain physician consultations, second opinions and treatment.
Miller said this will be even more pronounced with reduced access for low-income patients, those with multiple health problems and residents of rural communities. The CHQPR report also predicts the ASM is likely to increase Medicare spending rather than produce savings, since making it harder for patients to access care will result in more of these patients showing to for care in emergency rooms.
The ASM model cherry-picked geographic regions where it is being implemented, according to the report. Miller said the majority of areas covered by the ASM are rural and most of the largest cities in the country were excluded. Many of these rural communities have few, if any, cardiologists, pain medicine physicians or surgeons, so Miller does not see the logic in creating a system that would discourage treating these patients.
According to the CHQPR report, 6% of the areas included do not have any cardiologists. Areas with between one to two cardiologists made up 20% of areas CMS included in the ASM. Only 22% of the ASM regions have more than 10 cardiologists.

Two examples of rural counties chosen by CMS for mandatory participation in the new Medicare Ambulatory Specialty Model (ASM) for heart failure that have one cardiologist. If the cardiologist wants to avoid pay cuts and penalties by CMS, they could just stop seeing the small number of heart failure patients that make up their practice, but access to care will become more difficult for those patients with few options in surrounding counties.
"CMS claims that the ASM will encourage cardiologists to deliver higher-quality care for heart failure and that it will encourage orthopedic surgeons, neurosurgeons, pain medicine physicians, anesthesiologists and physiatrists to deliver higher-quality care for low back pain," Miller said. "What the ASM will actually do is discourage these specialists from treating Medicare beneficiaries, particularly low-income beneficiaries and patients who have the most serious and complex conditions. It will also discourage these specialists from providing services in the rural communities where the ASM will be implemented.
Instead of implementing the program, CHQPR suggests CMS should terminate it and create patient-centered payments for the care of chronic conditions.

Dave Fornell has covered healthcare for more than 17 years, with a focus in cardiology and radiology. Fornell is a 5-time winner of a Jesse H. Neal Award, the most prestigious editorial honors in the field of specialized journalism. The wins included best technical content, best use of social media and best COVID-19 coverage. Fornell was also a three-time Neal finalist for best range of work by a single author. He produces more than 100 editorial videos each year, most of them interviews with key opinion leaders in medicine. He also writes technical articles, covers key trends, conducts video hospital site visits, and is very involved with social media. E-mail: [email protected]